
Headaches & Conditions · 6 min read
Understanding Vertigo and BPPV
Why the room spins, what BPPV crystals have to do with it, when the neck is the real driver, and how care can help — explained by Dr. Jared Cohen, DC.


Quick answer
Vertigo is the false sensation that you or the room is spinning. The most common cause is BPPV, where tiny inner-ear crystals drift into the wrong canal and send false motion signals with certain head positions. Repositioning maneuvers resolve most BPPV, while neck-driven (cervicogenic) dizziness responds to treating the upper cervical spine.
What vertigo really is
Vertigo and BPPV get used interchangeably, but they are not the same thing. Vertigo is a symptom: the specific sensation that you or your surroundings are spinning or moving when they are not. It is different from lightheadedness (feeling faint) and from general unsteadiness. BPPV is one cause of vertigo — the most common one.
The spinning comes from a mismatch between the signals your inner ear, your eyes and your neck send the brain about where your head is in space. When one of those three sources sends bad information, the brain cannot reconcile it, and the world appears to move. Pinpointing which source is misfiring is the first job, because the right care depends entirely on why it is happening.
According to the National Institute on Deafness and Other Communication Disorders, balance disorders are common and BPPV is the most frequent cause of vertigo in adults, especially over 50. In our Coral Springs office we see it often enough that it has its own page: vertigo treatment.
BPPV: the most common cause of vertigo
Benign paroxysmal positional vertigo is a plumbing problem in the inner ear. Tiny calcium carbonate crystals (otoconia) normally sit on a membrane that senses gravity. When some break loose and drift into one of the semicircular canals, certain head positions make them tumble, and the canal reports motion that is not happening. The result is a brief, intense spin.
The hallmarks of BPPV:
- Spinning triggered by a specific head movement — rolling over in bed, looking up at a shelf, bending to tie shoes.
- Episodes that last seconds to a minute or two, then settle.
- Nausea or queasiness during an attack; unsteadiness afterward.
- Eyes that flick rhythmically (nystagmus) during the spin — something we look for in the exam.
- No hearing loss or ringing — those point to other inner-ear conditions.
The name tells the story: benign (not dangerous), paroxysmal (comes in bursts), positional (position triggers it). It is disruptive precisely because a glance upward can set the room in motion, but understanding that the trigger is mechanical is often a relief in itself. BPPV responds well to canalith repositioning maneuvers, which guide the crystals back out of the canal.

Cervicogenic dizziness: when the neck is the real driver
Not all dizziness is inner ear. The upper neck is packed with position sensors that tell the brain where the head is relative to the body. When those joints are stiff or irritated — after whiplash, from years of forward-head posture, or with chronic neck tension — the signals get noisy, and the brain reads the mismatch as unsteadiness or a floating, swimming sensation.
How it tends to differ from BPPV: the feeling is more ‘off balance’ than true spinning, it lasts minutes to hours rather than seconds, it comes with neck pain or stiffness, and it is provoked by neck movement or sustained positions (a long drive, a day at the screen) rather than by rolling over in bed. Headaches at the base of the skull are common. We wrote about those warning signs in neck tension might be telling you something.
Many patients have both: a BPPV episode that resolves, followed by lingering neck-driven unsteadiness because they spent two weeks holding the head rigidly still. Sorting the two out is why the exam covers the ears, the eyes and the neck together. Migraine can also produce vertigo (vestibular migraine), so we ask about migraine patterns too.
How we evaluate and treat vertigo and BPPV in Coral Springs
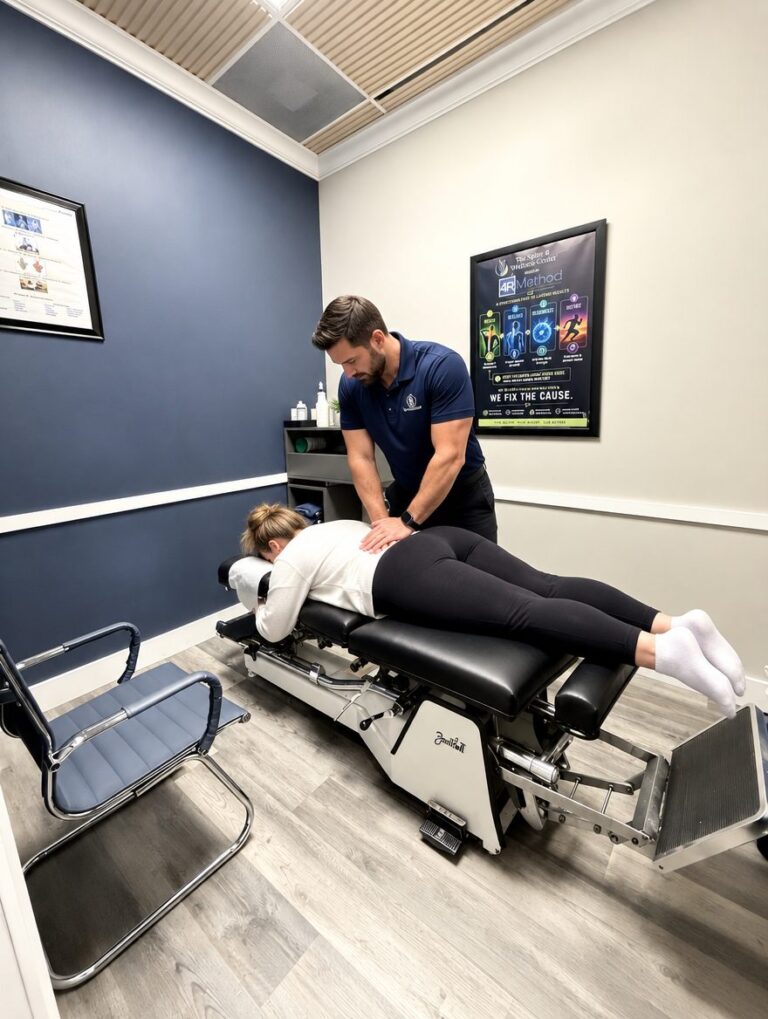
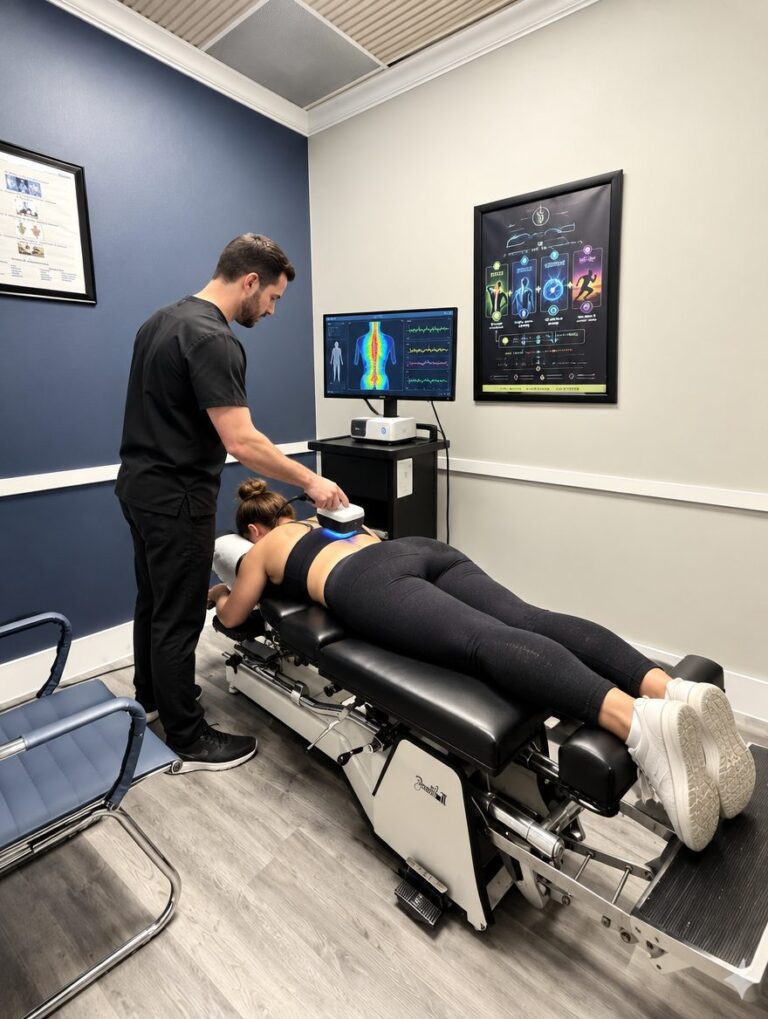
Visit one for vertigo and BPPV is measurement. We take a detailed history (what triggers it, how long it lasts, hearing changes, headaches, neck injuries), perform positional testing such as the Dix-Hallpike test to look for the nystagmus that confirms BPPV and identify which canal is involved, and examine the upper cervical spine hands-on with surface EMG and thermal scanning. Visit two is your full report of findings and plan.
Care then follows the 4R Method. In Repair, confirmed BPPV is treated with the appropriate repositioning maneuver (Epley or a canal-specific variant); most people need one to three sessions. Cervicogenic dizziness is treated with gentle upper-cervical adjustments, soft-tissue work and neck pain care. Rebuild adds vestibular and neck-proprioception exercises so balance is retrained, plus posture correction so the neck stops feeding bad data. Patients with tension-type headaches alongside dizziness usually improve together.
Some causes are not ours to treat. Sudden vertigo with hearing loss, double vision, slurred speech, facial weakness, a severe new headache, or trouble walking needs medical evaluation — please see a doctor or urgent care today. For everything else, a spine and balance assessment is the right starting point. We also serve many Parkland patients who first read our overview of vertigo care in Coral Springs.
Vertigo treatment
Positional testing, repositioning maneuvers and neck-driven dizziness care.
Learn moreNeck pain treatment
Upper-cervical care for the stiffness that feeds cervicogenic dizziness.
Learn moreHeadache treatment
For the base-of-skull headaches that so often travel with dizziness.
Learn moreChiropractic care
Gentle, specific adjustments as part of a measured plan.
Learn morePractical tips while you recover
- Move slowly through the positions that trigger you, but do not avoid movement entirely — holding the head rigid prolongs recovery.
- Sleep slightly propped up for a few nights after a repositioning maneuver if we advise it.
- Do not drive during an active episode, and sit down immediately when a spin starts.
- Keep the neck moving gently: slow chin tucks and rotations, within comfort.
- Stay hydrated and keep caffeine and alcohol moderate; both can worsen vestibular symptoms.
Key point
Vertigo is a symptom, not a diagnosis, and vertigo and BPPV are not synonyms. BPPV, cervicogenic dizziness and vestibular migraine feel different, last different lengths of time and need different care. A proper exam that checks the ears, eyes and neck together is what gets you to steadier days quickly.
Serving vertigo and dizziness patients across North Broward
Our clinic at 5675 Coral Ridge Drive, Coral Springs, FL 33076 serves Coral Springs, Parkland, Coconut Creek, Margate, Boca Raton, Tamarac, Pompano Beach and Deerfield Beach. Same-day appointments are usually available — call (954) 341-2256 or book online. Most patients from Parkland and Coral Springs are here in under 15 minutes.
Medically reviewed by Dr. Jared Cohen, DC — Co-Founder & Clinical Director, The Spine and Wellness Center. Last reviewed October 2026.
Frequently asked questions
How do I know if my dizziness is BPPV or something else?
BPPV produces brief, intense spinning triggered by specific head positions such as rolling over in bed, lasting seconds to a minute or two. Dizziness that feels more like unsteadiness, lasts longer, and comes with neck pain often points to the neck. Hearing loss, ringing, severe headache or neurological symptoms suggest other causes that need medical evaluation.
Can a chiropractor treat vertigo and BPPV?
Yes, within limits. We perform positional testing to confirm BPPV and treat it with canalith repositioning maneuvers, and we treat cervicogenic dizziness with gentle upper-cervical care and balance retraining. Vertigo with hearing loss, neurological signs or a sudden severe headache is referred for medical evaluation first.
How many treatments does BPPV take?
Most people with confirmed BPPV improve substantially within one to three repositioning sessions. Recurrence is possible over the years, so we teach you what an episode feels like and how to get back in quickly. Neck-driven dizziness usually takes longer, improving over several weeks as the neck joints and posture are corrected.
Why does my neck hurt when I am dizzy?
The upper neck contains position sensors that help the brain judge where the head is. Stiff or irritated upper cervical joints send inaccurate signals, which the brain experiences as unsteadiness. Neck pain and dizziness therefore often travel together, and treating the neck frequently improves both.


Same-day appointments
Reading about it is step one.
Step two is a measurement. Visit one we measure — and usually begin care; visit two you get your full findings and plan.
- Same-day appointments are usually available
- Our team calls you back to confirm your visit
- Coral Springs, serving Parkland & North Broward since 2005
Prefer to talk now? Call or text (954) 341-2256